
Hair Transplant for Women in Sri Lanka
Female hair loss — whether from diffuse thinning, hormonal changes, or traction alopecia — requires a specialist approach distinct from male hair restoration. At Dr. Hair, we offer tailored transplant solutions for women, including targeted hairline work and density restoration, all designed to complement female hair growth patterns and deliver natural, confidence-restoring results.
Hair Transplant for Women
Hair transplant surgery is far more widely discussed in the context of male hair loss than female. That gap does not reflect clinical reality. Female hair loss is common, frequently under-diagnosed, and often under-treated. This guide is for women who are researching hair restoration surgery in Sri Lanka and want to understand — before their consultation — what surgical candidacy actually means for women, why the assessment is more complex than it is for men, and what honest outcomes look like.
What is Female Hair Transplant?
Female hair transplant uses FUE or implanter pen technique to extract follicles from stable donor zones and implant them in areas of thinning or recession. The surgical technique is the same as male hair transplant. What differs is the diagnostic process before surgery. Determining whether a woman is a suitable surgical candidate requires a significantly more thorough assessment than is needed for most men — because the factors that make surgery safe and effective in women are harder to confirm.
A 2024 retrospective study across 60 female FUE patients found over 85% achieved graft survival rates exceeding 95% at 12 months. Patient satisfaction ran high: 41% of patients reported over 90% satisfaction with results. Surgery, when performed on the right candidate, works well for women.
How Female Hair Loss Differs from Male
Understanding this is essential before your consultation.
Male pattern hair loss follows the predictable Norwood scale: recession begins at the temples, progresses through the mid-scalp, and eventually affects the vertex. Critically, the back and sides of the scalp (the donor zones used in surgery) remain resistant to hair loss hormones throughout. This makes donor stability in men relatively straightforward to confirm.
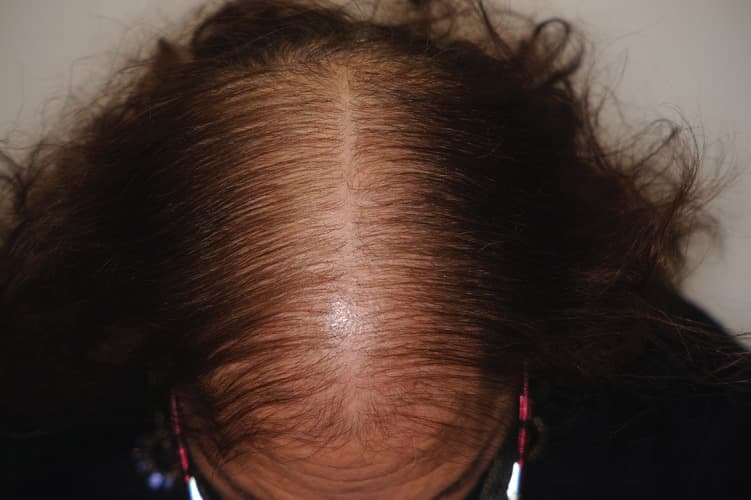
| Stage | What You See | Illustration |
|---|---|---|
| Ludwig I | Subtle widening of the central parting; scalp not prominently visible. Hair loss at this stage responds well to non-surgical treatment. |  |
| Ludwig II | More pronounced part-line widening; scalp visible when hair is parted. Medical and in-clinic treatment recommended. |  |
| Ludwig III | Diffuse thinning across the top and crown; scalp clearly visible. Surgical assessment alongside medical therapy is recommended at this stage. | 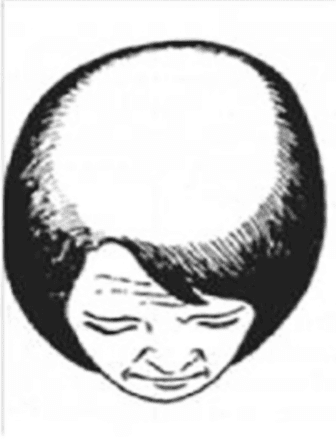 |
Fig. 1 — Ludwig scale stages of female pattern hair loss (FPHL): Stage I shows subtle central parting widening; Stage II shows increased scalp visibility; Stage III shows diffuse thinning across the crown. Recognising your stage early improves treatment outcomes. (Source: Fabbrocini et al., Int J Womens Dermatol 2018; PMC6322157)
The key difference: female hair loss is diffuse rather than patterned. This means it may affect the donor zones at the back and sides of the scalp that male patients rely on as their safe extraction area. A woman who appears to have good hair at the back of her scalp may have significant follicle miniaturisation in that zone — and transplanting miniaturised follicles produces grafts that will themselves thin and fail over time.
This is why the assessment for female candidacy is more extensive, and why women are more frequently found to be unsuitable surgical candidates than men.
What Makes a Woman a Good or Poor Surgical Candidate?
The most important clinical distinction in female hair transplant candidacy is between two patterns:
Diffuse Patterned Alopecia (DPA): Hair loss follows a recognisable pattern confined to the top of the head, with thinning spread throughout the pattern area rather than focused on specific regions. The temporal, parietal, and occipital donor zones remain intact. These women may be viable surgical candidates.
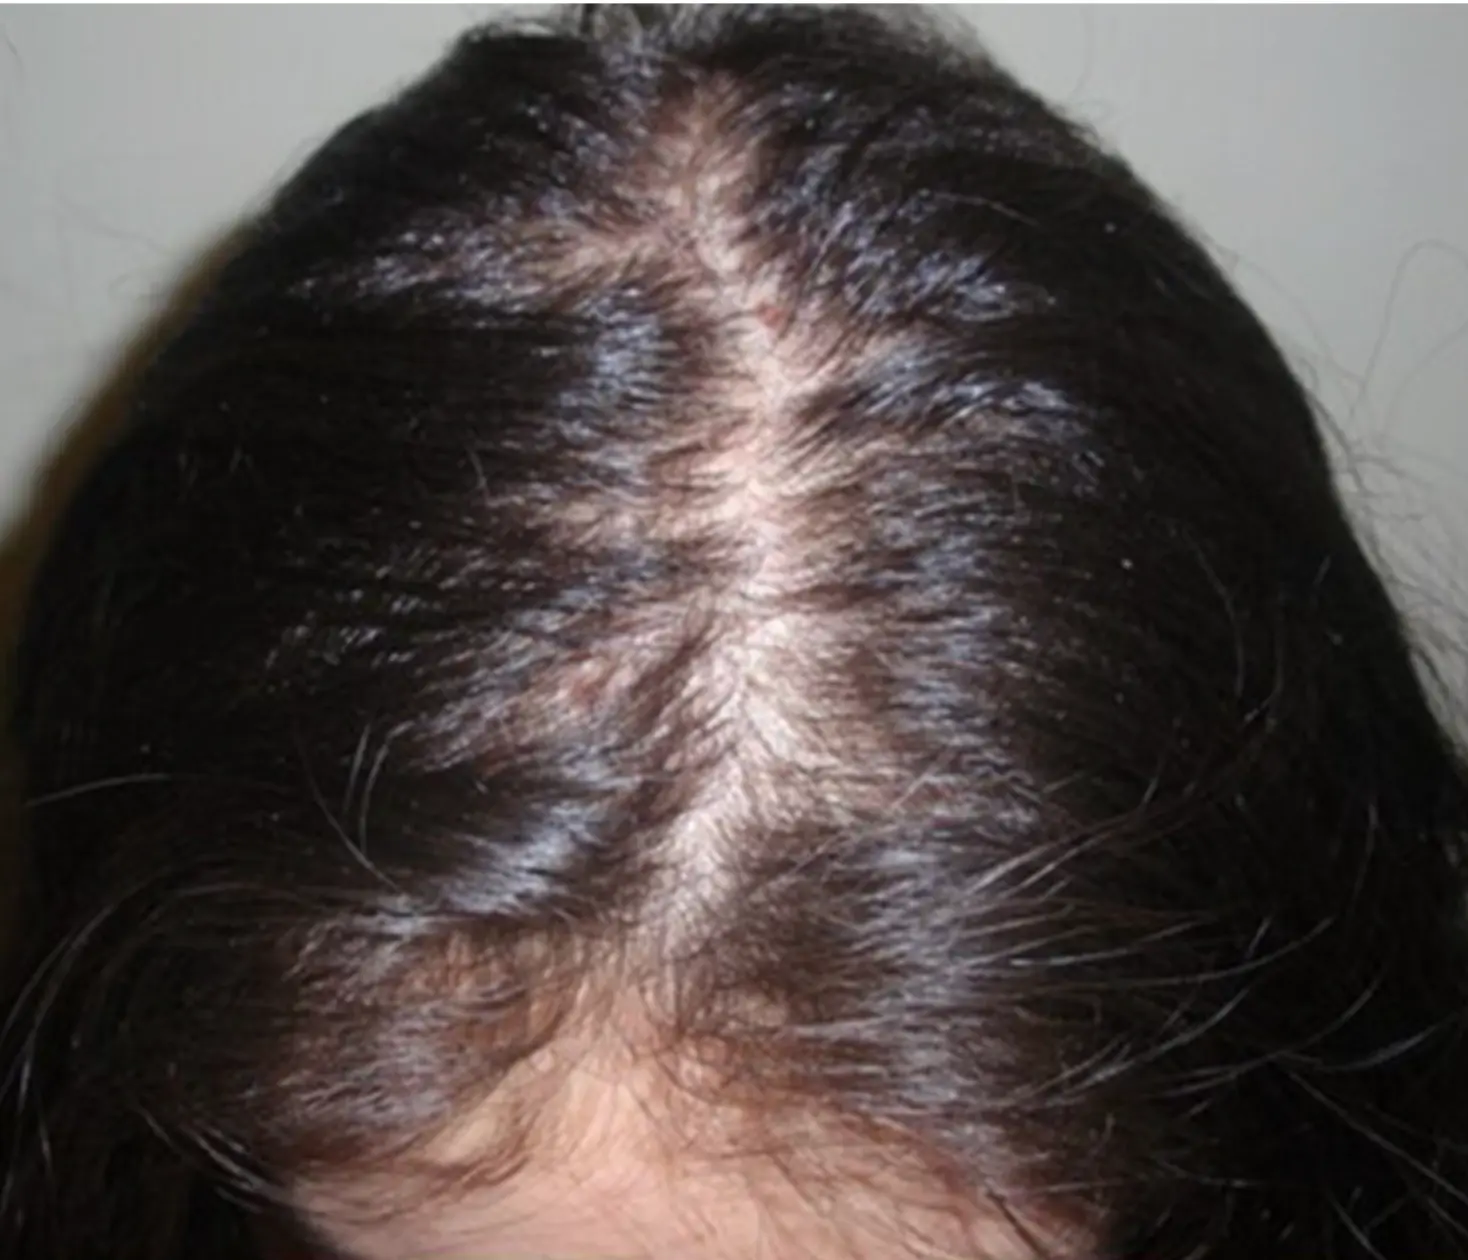
Diffuse Unpatterned Alopecia (DUPA): Miniaturisation and density loss are not confined to the top of the head; they extend into the temporal, parietal, and occipital scalp areas that form the donor zone. The principle of donor dominance underpins all hair transplant surgery: if there is no safe donor area, transplantation will not succeed. Surgery is contraindicated.
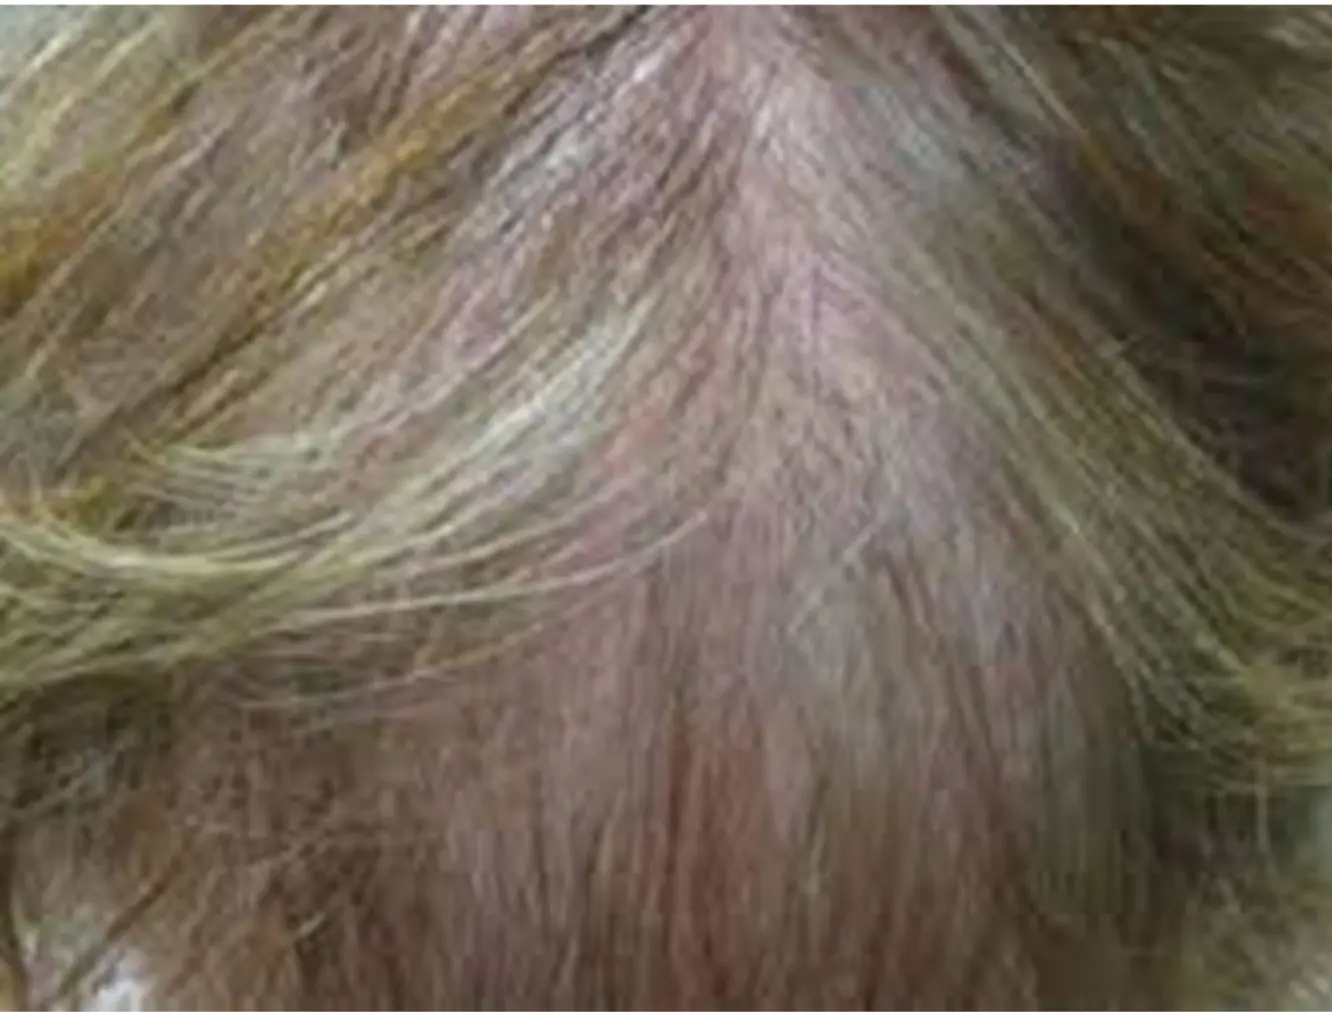
Distinguishing DPA from DUPA cannot be done by visual examination or a photograph. It requires trichoscopy and densitometry of the donor zone. This is a non-negotiable part of the assessment process.
Why Hormones and Systemic Health Matter
Female hair loss has a significantly higher rate of systemic and hormonal contribution than male pattern loss. Before any surgical plan is made, the following should be assessed:
- Thyroid function — both hypothyroidism and hyperthyroidism cause diffuse hair loss that mimics FPHL
- Ferritin and iron studies — iron deficiency is the most commonly missed cause of prolonged hair shedding in women; it is treatable and should be ruled out before surgery
- Sex hormones — elevated androgens (testosterone, DHEAS) may indicate polycystic ovary syndrome (PCOS), which drives hair loss and must be managed alongside any surgical plan
- Vitamin D and B12 — both deficiencies contribute to poor hair quality and shedding
- Prolactin — elevated levels can trigger hair loss
A consultation that does not cover these is incomplete. If you have had blood tests for hair loss before, bring the results. If you have not, ask whether they should be part of your assessment.
What Results Look Like for Women
The timeline for female hair transplant results follows the same pattern as male surgery:
| Timeline | What Happens |
|---|---|
| Weeks 2 to 4 | Shock loss — transplanted hairs shed temporarily |
| Month 3 to 4 | New growth begins; fine initially |
| Month 6 to 9 | Clear improvement visible, especially along the parting line |
| Month 12 to 18 | Full result; density normalised |
Female transplants are often more targeted than male procedures, addressing specific zones (parting line, temple, hairline) rather than broad coverage. A well-planned female procedure producing improvement in parting line density or a refined hairline edge creates a visible improvement that patients typically describe as natural and satisfying.
Common Female Hair Loss Presentations That Surgery Addresses
| Condition | Surgical Approach |
|---|---|
| Female pattern hair loss (confirmed DPA) | Density improvement at parting line and crown |
| Frontal hairline recession | Hairline restoration and temporal peak refinement |
| Post-traction alopecia | Targeted repair of recession at temples or edges |
| Congenitally high forehead | Hairline lowering |
| Scarring alopecia (stable, confirmed) | Follicle transplant into scarred zones |
What to Do If You Are Told You Are Not a Candidate
Being told you are not a surgical candidate is not the end of the road. The most common reasons are:
- Donor zone miniaturisation (DUPA): Your donor follicles are themselves thinning. Surgery would use unstable grafts that fail over time. Non-surgical options (PRP, mesotherapy, medical therapy) are the appropriate path.
- Active hair loss progression: Hair loss is still changing. Medical stabilisation for 6 to 12 months is needed before surgery is reconsidered.
- Unresolved systemic factor: An iron deficiency, thyroid issue, or hormonal imbalance is driving the loss. Treating the cause first may restore significant density without surgery.
If you are told you are not a candidate and you want a second opinion, that is completely reasonable. Bring your trichoscopy results and blood panel if you have them.
Questions to Ask at Your Consultation
- Based on my trichoscopy, do I have DPA or DUPA? What does the donor zone assessment show?
- Are there any systemic factors contributing to my hair loss that should be addressed before surgery?
- Am I above or below the 15% miniaturisation threshold that requires medical therapy before surgery?
- Is my hair loss pattern stable, or am I still in an active phase?
- Would non-surgical treatment (PRP, mesotherapy, medical therapy) produce results comparable to surgery in my case?
- Do I need to shave my head for this procedure?
Frequently Asked Questions
Am I a good candidate for hair transplant as a woman?
Candidacy depends on whether you have a stable, patterned form of hair loss with a healthy donor zone. Women with diffuse unpatterned alopecia affecting the donor zone are not surgical candidates. The only way to confirm candidacy is trichoscopy and a thorough clinical assessment.
Do women need to shave their head for hair transplant?
Not necessarily. Implanter pen technique allows transplantation without shaving the recipient area. For FUE, only the donor zone (typically a strip at the back) requires trimming. Women are told exactly what is required before confirming any procedure.
Can hair transplant fix thinning at the parting line?
Yes, for women with confirmed DPA. Targeting the central parting and crown with precise implanter pen technique implantation is one of the most effective surgical applications in women. Results at 12 months show meaningful improvement in perceived density at the parting.
What if my hair loss is hormonal?
Hormonal hair loss in women (PCOS, thyroid, post-partum) often improves significantly with medical management of the underlying cause. Surgery is rarely the first step. Your assessment should include hormonal testing, and if a correctable cause is found, it should be treated first. Many women achieve satisfying improvement through medical management alone.
Is the result permanent?
Hair transplantation can provide long-lasting results by using healthy follicles from the donor area. However, the native hair surrounding the transplanted area may continue to thin if the underlying cause of hair loss is not managed. Depending on your individual needs, ongoing medical treatment may be recommended alongside surgery.