

PRP Hair Treatment in Sri Lanka: What It Is and What to Expect

In This Article
- What PRP Is and How It Is Meant to Work
- Does PRP Actually Work? What the Evidence Shows
- What PRP Can and Cannot Do, and What Results Look Like
- What Happens During a Session, and How Many You Need
- Is PRP Safe? Side Effects and Who Should Avoid It
- Where PRP Fits Among Your Options
- Getting PRP in Sri Lanka: What to Check Before You Book
- Frequently Asked Questions About PRP Hair Treatment
- Does PRP really regrow hair, or is it a scam?
- How many PRP sessions do I need for hair?
- Is PRP hair treatment painful?
- Does PRP work for women's hair loss?
- How long do PRP results last?
- Is PRP FDA-approved for hair loss?
- Can I have PRP instead of a hair transplant?
- The Bottom Line
PRP (platelet-rich plasma) hair treatment uses a concentrate made from your own blood, injected into the scalp to stimulate follicles that are thinning but still alive. It is non-surgical, delivered as a course of sessions, and it works best to strengthen and preserve existing hair rather than to regrow hair on scalp that is already bald. The pooled evidence is genuinely positive but not settled, PRP is not FDA-approved for hair loss, and no two clinics necessarily prepare it the same way. Here is what it is, what the research shows, and what to expect if you have it done in Sri Lanka.
What PRP Is and How It Is Meant to Work
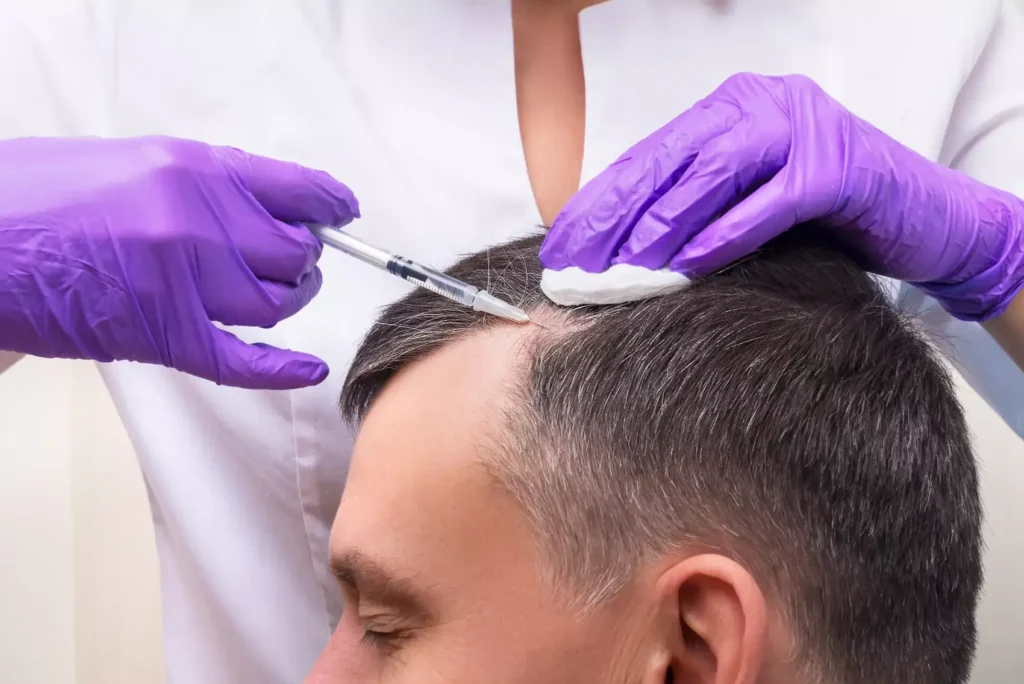
Platelets carry growth factors, the signalling proteins your body uses to trigger tissue repair. PRP concentrates them into a small volume of plasma and delivers them where follicles are weakening. In clinic that means three steps: blood is drawn into a tube containing an anticoagulant such as sodium citrate, the sample is spun to separate the platelet-rich fraction from red cells and platelet-poor plasma, and the concentrate is injected across the thinning areas once the scalp is numbed. Because it is your own blood, PRP is autologous: no foreign substance, no rejection, no donor.
Concentration is the point, and nobody agrees on the right number. A 2022 review in Frontiers in Medicine describes PRP as carrying a three- to five-fold increase in growth factors over whole blood, targeting around one million platelets per microlitre in five millilitres of plasma; a 2023 review in Biomedicines recommends 1 to 1.5 million per microlitre; the International Society of Hair Restoration Surgery (ISHRS) says two to six times baseline while stating no consensus exists. Published studies actually achieved 1.5 to seven times baseline. Nor is “PRP” one product: the literature recognises four classes, and comparative data on which is best for hair is lacking.
Mechanistically, platelet alpha-granules hold roughly 13 bioactive substances and release at least 95% of their growth factors within an hour of degranulation. In laboratory work IGF-1 and EGF together push follicles from telogen (rest) into anagen (growth) and upregulate Wnt/beta-catenin signalling, while VEGF and PDGF increase blood supply around the follicle. There is tissue evidence too: in a randomised, evaluator-blinded, placebo-controlled half-head trial in STEM CELLS Translational Medicine (Gentile et al., 2015, 23 enrolled, 20 completing), biopsies from PRP-treated areas showed significant increases (p < 0.05) in epidermal thickness, follicle numbers, proliferating cells and small blood vessels.
Note what the mechanism does not include. Nothing in it blocks DHT, and nothing in it creates a follicle that no longer exists. PRP is a stimulus applied to living tissue. I spell out the difference between a miniaturising follicle and a dead one in is my hair loss reversible.
Does PRP Actually Work? What the Evidence Shows
This is the section most PRP pages leave out, and it is the one that should decide whether you spend money. The honest summary: the pooled signal is positive and consistent across independent teams, and most of those teams rated their own evidence low quality.
| Source | Design | Main finding | Caveat the authors flag |
|---|---|---|---|
| Dermatology and Therapy, 2025 (Anitua et al.) | Meta-analysis, 43 RCTs, 1,877 participants | Activated PRP increased density vs placebo and reduced hair loss | Called moderate evidence, but no significant effect on thickness, substantial heterogeneity, and the authors work for a PRP technology company |
| Anais Brasileiros de Dermatologia, 2024 | Meta-analysis, 14 RCTs, 431 patients | +27.55 hairs/cm² vs control (95% CI 14.04 to 41.06) | GRADE LOW for density, VERY LOW for diameter; I² = 95.99%; funnel plot asymmetry indicating publication bias |
| Aesthetic Plastic Surgery, 2023 | Meta-analysis, 10 RCTs, 318 participants | +25.09 hairs/cm² (95% CI 9.03 to 41.15, p = 0.002) | Substantial heterogeneity; saline controls may themselves trigger wound healing |
| Journal of Dermatological Treatment, 2022 (Evans et al.) | Systematic review, 30 studies, 687 patients | 29 of 30 studies reported benefit; 24 reached significance | Authors still called for low risk-of-bias RCTs to optimise protocols |
| Frontiers in Pharmacology, 2021 | Systematic review, 42 studies, 776 women | Density vs placebo OR 1.61, interval crossing 1 (95% CI 0.52 to 2.70) | Evidence in women weaker than in men; I² above 75% |
| Acta Dermato-Venereologica, 2020 (Gressenberger et al.) | Randomised placebo-controlled trial, 30 men | No benefit: median density -9.0 hairs/cm² at six months, not significantly different from saline (p = 0.366) | PRP as monotherapy does not improve hair growth in men |
Density improves; thickness does not. The 2025 review of 43 trials states plainly that PRP did not significantly affect hair thickness. The 2024 meta-analysis found a diameter difference of just 2.02 micrometres with a confidence interval crossing zero (95% CI -0.85 to 4.88), and the 2023 meta-analysis agreed (SMD 0.57, 95% CI -0.23 to 1.38, p = 0.16). PRP may increase how many hairs you have per square centimetre; that it thickens each strand is not supported by pooled data.
Small studies flatter PRP. In the 2023 analysis, trials with 30 or fewer participants reported a density gain of 40.64 hairs/cm² (95% CI 23.67 to 57.61); trials with more than 30 reported 9.57 (95% CI 6.38 to 12.76). Combined with the publication bias flagged in 2024, that is a warning the real-world benefit sits nearer the low end.
At least one good trial found nothing. Gressenberger randomised 30 men to PRP (20) or saline (10), gave five treatments at four to six week intervals, and at six months found no significant difference in density or diameter. Around 68% of the PRP group still felt their hair had improved, which tells you how much weight to put on before-and-after impressions, including your own.
PRP looks better as an add-on than as a solo act. A 2024 meta-analysis in PLOS ONE of five RCTs found PRP plus topical minoxidil ahead of minoxidil alone at every timepoint: +11.07 hairs at one month (95% CI 1.20 to 20.94), +21.81 at three months (95% CI 10.64 to 33.00) and +17.80 at five to six months (95% CI 7.91 to 27.69). But the authors graded that evidence low to very low, only one trial had a low risk of bias, and follow-up never exceeded six months. Encouraging, not conclusive.
One more note, because it cuts against my own commercial interest: a 2020 letter in the Journal of the European Academy of Dermatology and Venereology reported that PRP used alongside hair transplantation showed no benefit. It is not automatically a useful add-on to surgery, and I explain how I think about that in PRP after a hair transplant.
What PRP Can and Cannot Do, and What Results Look Like
This is where honesty matters most, and it is the same distinction I draw in PRP or hair transplant:
- PRP can improve the density and appearance of existing coverage and help hold ground against ongoing loss. It supports follicles that are alive but under-performing.
- PRP cannot create hair where the follicle is gone. A bald, smooth area of scalp will not respond, because there is nothing left there to stimulate.
Any promise that PRP regrows a bald scalp is not supported by the biology. The ISHRS says the best candidates have thinning hair rather than complete baldness and more recent loss, and that available data suggest at least 30 to 50% of patients will experience some benefit, which is a very different sentence from “PRP works”. In my practice at Dr. Hair, the patients who come away satisfied almost always arrived early, with visible thinning but a scalp that still has hair on it everywhere you look. The ones who come away disappointed booked PRP hoping to avoid a conversation about surgery, when the shine on the crown had already answered the question.
Where it works, PRP is reinforcement rather than transformation. The ISHRS advises that improvement may appear as early as one to two months but can take as long as six, and typically shows up as decreased shedding or thicker-appearing hair rather than dramatic regrowth. That matches what I see. The first thing patients report is not new hair, it is that the drain and the pillow are cleaner.
The spread of published results explains why nobody can promise you a figure. A 2025 review in Medical Sciences notes density improvements ranging from +8.1 to +19 hairs/cm² at three months and +23.1 to +49.4 at six months, with at least one study finding no improvement in terminal hair density at all. At the strong end, the 2015 half-head trial reported a mean total density increase of 45.9 hairs/cm² against baseline, from 20 completers. Results also fade, which is the honest reason maintenance exists rather than a commercial one: in that trial’s two-year follow-up, four patients reported progressive loss returning at 12 months after their last treatment and were re-treated.
What Happens During a Session, and How Many You Need
Expect an appointment to run somewhere in the region of an hour, most of it preparation and numbing rather than injection. That is an in-clinic estimate, not a published standard; no credible source specifies a duration. The published parameters vary widely, which is worth knowing before you compare two clinics:
- Blood volume drawn: across 42 studies in women this ranged from 9 mL to 120 mL, narrowing to 10 to 40 mL across RCTs published between 2020 and 2024, yielding 1 to 5 mL of finished PRP.
- Spin protocol: single-spin has been reported at 900 to 3,000 rpm for 10 to 15 minutes; double-spin adds a shorter second spin at 2,000 to 2,500 rpm. A 2025 meta-analysis in Frontiers in Medicine of three RCTs (90 participants) compared the two and found neither difference statistically significant (density 4.10% in favour of single-spin, 95% CI -4.74 to 12.93, p = 0.36). A clinic claiming its centrifuge explains its results is overstating what is known.
- Activation: PRP may be activated with calcium chloride, thrombin or autologous serum, and many protocols skip it. The 2025 review of 43 RCTs found activated PRP effective against placebo and more frequent adverse effects without activation. Given that team’s industry affiliation, treat it as a reasonable working preference, not a settled fact.
- Injection technique: reported needle gauges are commonly 22 to 30G, depth around 1.5 to 2.5 mm intradermally (about 0.5 mm by microneedling), points roughly 1 cm apart, about 0.2 mL per site. The ISHRS describes quantities as small as 0.05 mL per point, allowing as many as 120 sites in one procedure.
PRP is a course, not a one-off. The most commonly used protocol is three sessions one month apart followed by boosters roughly every six months, though the ISHRS states explicitly that no standard interval exists. A 2018 review in the International Journal of Women’s Dermatology proposes monthly for three months then quarterly, giving six sessions in year one. A 2023 umbrella review of 28 articles in the Journal of Cosmetic Dermatology concluded effective treatment needs at least 0.05 mL/cm² of PRP, preferably 0.1, and at least three consecutive monthly treatments.
At Dr. Hair we work from that three-then-maintenance framework and adjust after assessing your scalp and your response. I will not quote you a fixed number before I have looked at your hair, because a course that suits early diffuse thinning is not the course that suits someone with two years of steady loss behind them. You can see how this sits within our PRP hair therapy service.
Is PRP Safe? Side Effects and Who Should Avoid It
Safety is comfortably the strongest part of the PRP story. Because the preparation is autologous and made on the day, immunogenic risk is minimal, and across meta-analyses no intolerable or high-risk adverse effects have been reported. Documented effects are mild and self-limiting:
- Pain at the injection sites, usually brief
- Swelling, redness and temporary scalp sensitivity
- Minor bleeding or bruising, typically resolving within four to five days
- Mild headache
The review of 42 studies covering 776 women documented no serious adverse events, and the Gressenberger trial described swelling, redness, minor bleeding, haematoma and pain as fully reversible. Adding PRP to topical minoxidil produced no increase in adverse event risk versus minoxidil alone (OR 0.55, 95% CI 0.22 to 1.36). A short-lived shed afterwards is possible but uncommon, and I have no reliable incidence figure for it.
PRP is still not for everyone. Absolute contraindications include critical thrombocytopenia, platelet dysfunction, haemodynamic instability, sepsis and active infection at the injection site. Relative contraindications reported in the literature include recent NSAID or systemic corticosteroid use, recent illness or fever, cancer, anaemia with haemoglobin below 10 g/dL, a platelet count below 150,000/µL, and tobacco use. That is why PRP should be preceded by a medical history rather than a booking form. Low risk is not the same as no assessment.
Where PRP Fits Among Your Options
PRP is rarely the whole answer on its own. It often works best alongside medical treatment such as minoxidil for hair loss, and the strongest PRP data we have is precisely the combination data. It is one part of our broader hair restoration services.
| PRP | Topical minoxidil | Hair transplant | |
|---|---|---|---|
| What it does | Stimulates existing, weakening follicles | Prolongs the growth phase of existing follicles | Relocates DHT-resistant follicles into bald or thin areas |
| Works on bald scalp? | No | No | Yes, this is what it is for |
| Regulatory status | Not FDA-approved for hair loss; off-label per ISHRS | FDA-approved for androgenetic alopecia | Surgical procedure, not a drug approval question |
| Strength of evidence | Positive pooled effect on density, certainty low to moderate; no effect on thickness | Established from large randomised trials | Established; depends on planning and donor supply |
| Ongoing commitment | Maintenance sessions; benefit fades after stopping | Indefinite daily use | One-off, though native hair still needs protecting |
| Typical candidate | Recent, visible thinning with follicles still present | Early diffuse thinning | Established recession or baldness with a stable donor area |
On a comparison people often ask me to make: there is no head-to-head randomised trial of PRP against oral finasteride, so I cannot tell you which is better and neither can anyone else. They address different points in the same process, and treating them as rivals is usually a mistake. Our hair loss treatment assessment exists to work out which of those three columns you belong in.
Getting PRP in Sri Lanka: What to Check Before You Book
PRP is widely offered in Colombo and beyond, and I want to be careful here: there is no published Sri Lankan data on how many clinics offer it, how many patients have had it, or what results they got. Anyone quoting you a local success rate is quoting a number that does not exist in any verifiable source, including me.
What you can do is ask better questions, because PRP is not standardised. Across 11 RCTs published between January 2020 and May 2024 covering 684 participants, courses ranged from three to six sessions and intervals from two weeks to monthly, alongside varying blood volumes and spin methods. One investigation of three commercial collection systems found two produced plasma with a lower platelet concentration than whole blood. Two clinics can both offer “PRP” and deliver materially different things. Before you book anywhere, including here, I would ask:
- Who is performing it? Medical practitioners here are regulated by the Sri Lanka Medical Council, the statutory body responsible for the profession and for upholding ethical standards. You are entitled to know a qualified, registered doctor is doing the assessment and the injections. Internationally, PRP is often administered by non-physicians.
- Have you diagnosed me before selling me a course? PRP is for androgenetic thinning with viable follicles. If nobody has examined your scalp and taken a history, the recommendation is not a clinical one.
- What protocol do you use? Blood volume, spin method, whether the PRP is activated, and whether platelet concentration is measured at all.
- What are you promising? Any claim of guaranteed regrowth, or regrowth on a bald area, is one the literature does not support.
One regulatory point deserves precision because marketing routinely misrepresents it. PRP is not FDA-approved for hair loss. What is cleared under the 510(k) pathway is the preparation equipment, largely for orthopaedic indications, and the ISHRS states plainly that use for hair growth is off-label because no data sufficient for that indication has been submitted.
Frequently Asked Questions About PRP Hair Treatment
Does PRP really regrow hair, or is it a scam?
Neither extreme is right. Independent meta-analyses find a real pooled increase in density, roughly 25 to 28 hairs per cm² versus control, so it is not a scam. But heterogeneity is extreme, publication bias is documented, several reviews grade their own certainty as low or very low, and a placebo-controlled trial of 30 men found no benefit from PRP alone. Treat it as a plausible, low-risk intervention with modest expected benefit, not a proven cure.
How many PRP sessions do I need for hair?
The most widely used protocol is three sessions one month apart, then boosters around every six months; an alternative published schedule is monthly for three months then quarterly, totalling six in year one. An umbrella review of 28 articles concluded at least three consecutive monthly treatments are needed for an effect. The ISHRS is explicit that no standard interval exists, so your schedule should be set after an assessment rather than sold as a fixed package.
Is PRP hair treatment painful?
There is discomfort, but it is brief. The scalp is numbed first, and the most consistently reported side effect across the literature is short-duration local pain at the injection sites. Swelling, redness, minor bleeding and a mild headache afterwards are common but fully reversible. Most patients return to normal activity the same day.
Does PRP work for women’s hair loss?
The evidence in women is weaker than in men. A systematic review of 42 studies covering 776 women with female pattern hair loss found density versus placebo at an odds ratio of 1.61 with a confidence interval crossing 1 (95% CI 0.52 to 2.70), and versus baseline 1.11 (95% CI 0.86 to 1.37), with heterogeneity above 75%. That does not mean it cannot help a given woman, but I set expectations more cautiously and always look for a treatable underlying cause first.
How long do PRP results last?
Not indefinitely. In the two-year follow-up of the 2015 trial, four patients saw progressive loss return at 12 months after their last session, more evident by 16 months, and needed re-treatment. There is very little long-term data beyond that, and no trial has established the optimal maintenance interval. Plan for PRP as ongoing maintenance, as you would topical medication, not a one-time fix.
Is PRP FDA-approved for hair loss?
No. The devices used to prepare it are cleared under the 510(k) pathway, largely for orthopaedic applications, and that clearance only establishes the equipment is safe and substantially equivalent to an existing device. The ISHRS describes use for hair growth as off-label. Any clinic implying FDA endorsement of PRP for hair is misdescribing the regulatory position.
Can I have PRP instead of a hair transplant?
Only if your follicles are still there. PRP stimulates living follicles; it cannot create one that has gone. If your thinning is recent and diffuse, PRP is reasonable to try, ideally alongside medical therapy. If you have smooth, established baldness, PRP will not address it, and a course of injections simply delays the decision you actually need to make.
The Bottom Line
PRP is a low-risk, autologous treatment with a genuine but modest benefit for androgenetic thinning. Independent meta-analyses point the same way, an increase in density of roughly 25 to 28 hairs per cm² over control. The largest and newest calls that evidence moderate, though its authors work for a PRP technology company; the earlier ones rate their own low or very low and flag extreme heterogeneity and publication bias. Gains in hair thickness are not statistically robust in any of them, one good placebo-controlled trial found no benefit from PRP alone, the benefit fades without maintenance, and PRP is not FDA-approved for hair loss whatever the marketing suggests.
None of that makes it a bad treatment. It makes it a treatment with a specific job. If your hair is thinning but still present, particularly if the loss is recent, PRP is worth a serious look, especially combined with medical therapy. The only way to know which camp you are in is a scalp assessment by someone willing to tell you the less profitable answer.
Book a consultation at Dr. Hair and we will assess your scalp, tell you honestly whether PRP is likely to help, and set out what a realistic course would look like, including the possibility that PRP is not the right tool for you at all. Not a sales pitch.
Book a PRP Consultation at Dr. Hair →
Written by Dr. Tharindu, Hair Transplant Specialist at Dr. Hair Sri Lanka